
Clinical Psychology Research Topics: Narrow Questions for a Pakistani Thesis

Which clinical psychology research topics can a student in Pakistan finish within one degree? Before committing, settle a few things. Can I test an Urdu screening scale without a hospital partner? Which option needs a trained interviewer, and which runs on a questionnaire? How do I design a self-harm study that my ethics committee will approve? Is a trial already running on my idea?
The topics below answer those questions through named studies. Each one gives the data route, the level it suits and the usual trap. The list covers adult and adolescent clinical work in Pakistani settings, so child, forensic and neuropsychological work sit outside it. For the other branches, start with the wider psychology research topics list.
For a narrower list, try IO psychology research topics, which covers workplace behaviour and organisations. A deeper set sits in developmental psychology research topics, which covers child and adolescent development. Related ideas appear in forensic psychology topics for courts and justice, which covers courts, evidence and criminal justice.
Clinical psychology research topics grouped by the data they need
Access, not interest, decides most clinical theses. For that reason, the topics are grouped by what you must get hold of. Measurement topics need participants and sometimes a trained interviewer. Trauma topics need community permission. Intervention topics need a partner programme. Law topics need documents and clinicians willing to talk.
Every topic rests on a study you can read. However, a study is only a starting point. Read the full paper, check whether a correction exists, and search for newer work. The right design also depends on choosing a research methodology that your supervisor can examine.
Urdu screening tools: cutoffs, wording and structure
Screening scales make practical first projects because they need questionnaires rather than treatment access. However, the strongest versions add a clinical interview, so check what your department can supervise.
1. Test-retest reliability and concurrent validity of the Urdu GAD-7 in university students
In 2026, Khan, Madihie and Ali published an adaptation of the GAD-7 tested on 267 adults receiving treatment at private psychiatric clinics in Peshawar, Abbottabad, Islamabad and Karak. The authors name what they left out. They did not assess test-retest reliability, and they used no comparator scale. They suggest testing concurrent validity against the Aga Khan University Anxiety and Depression Scale.
A thesis can take that gap. Give the Urdu GAD-7 twice, one to two weeks apart, to a non-clinical university sample. Add the Aga Khan University scale once. Report reliability and concurrent validity, but not diagnostic accuracy, because a non-clinical sample cannot support clinical cutoffs. The design suits a final-year BS project or an MS dissertation.
Read the results table before citing a figure. The abstract gives a sensitivity of 98.6% at a cutoff of 10, while the table shows 97.6%. The journal has also issued a correction to how the paper describes the earlier Urdu validation by Ahmad and colleagues. As a result, cite the corrected version.
2. Where the Urdu PHQ-9 cutoff falls in a third patient group
Two studies show why a cutoff cannot be borrowed. Among 1,731 rural pregnant women near Rawalpindi, the Urdu PHQ-9 performed well at a score of 10 or more against a structured interview, with 94.7% sensitivity and 88.9% specificity. Among 150 patients with coronary artery disease, the best balance came at 6 or more, with 76% for both measures.
A thesis can add a third group, for example adults with type 2 diabetes attending one outpatient clinic. Report accuracy at several cutoffs, using a structured interview as the reference standard. Add a second assessor who is blind to the PHQ-9 score. The pregnancy study lists the lack of blinding as its own limitation, so this design fixes a known weakness.
The level is MS or MPhil, because you need a trained interviewer and a sample size built from expected prevalence. Do not present a clinic-based cutoff as a national norm.
3. How low-literacy and non-Urdu-first adults read anxiety items
Translation alone does not settle meaning. The expert panel behind the Urdu GAD-7 judged that the idea of feeling “on edge” has no direct Urdu parallel. It also found that “relaxing” can suggest idleness, and that women may under-report irritability because of norms around patience. In the PHQ-9 study, the team swapped difficult Urdu words for simpler ones and piloted the scale with 250 pregnant women before use.
A cognitive-interview study can test this directly. Ask adults to read each item aloud, explain it in their own words and say what it would look like in daily life. Recruit adults whose first language is not Urdu, because the 2026 validation required fluency in Urdu. Analyse item-level misreadings by content analysis, then propose revised wording to a bilingual panel.
This is a qualitative MS or MPhil project. Do not revise the item wording and then report the original scale’s validity as if nothing had changed.
4. Does the Urdu GAD-7 work the same way for women and men?
The 2026 validation tested measurement invariance across two age groups, younger adults (177) and older adults (87), and reported full invariance. Its sample was 60.2% female, yet it did not report invariance by sex. One-factor and two-factor models both fitted, with the two factors correlating at 0.88, and the authors kept the one-factor model.
A multi-group confirmatory factor analysis by sex would extend that work. Use an estimator suited to ordinal items, as the original did in R with lavaan, then compare configural, metric and scalar models. Multi-group models need larger samples than a single validation, so ask your supervisor to check power before you collect data.
The level is MPhil or PhD. Expect the irritability item from the previous topic to be the first to misbehave, so plan to test partial invariance.
After the floods: trauma measurement and care pathways
Flood research in Pakistan has moved from counting distress to testing how care reaches people. The three topics below take that shift further, including one repeat-survey design.
5. Do self-report cutoffs overstate PTSD after disasters?
Two Pakistani studies paint different pictures. A survey of 270 flood-affected residents in Khyber Pakhtunkhwa, run from March 2021 to May 2022, reported PTSD in 96% of respondents on a 17-item checklist. A household survey of 305 adults in Hassanabad, Hunza, in August 2024 used the Impact of Event Scale-Revised with a cutoff of 33. It found PTSD in 56.6%, while anxiety and depression were each near 15%.
The gap invites a measurement question. Give flood-exposed adults a PTSD self-report scale and a structured clinical interview, such as the CAPS-5, then compare the classifications at several cutoffs. The CAPS-5 needs trained raters, so this is an MPhil or PhD design, or an MS project inside a supervised team.
Be fair to both papers, because neither claims an error. The Hunza source is a conference abstract, so ask the authors for full methods before you build on it.
6. What happens between flood screening and treatment?
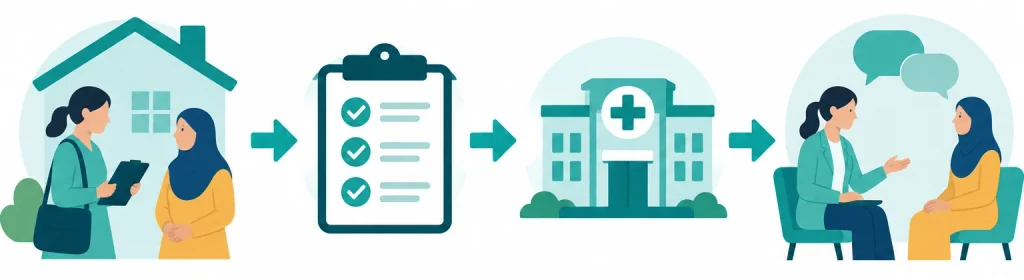
The 2022 monsoon floods affected more than 33 million people, and Sindh bore much of the impact. In Dadu, an Aga Khan University project had Lady Health Workers screen women of reproductive age with the GAD-2 and PHQ-2. Women scoring 3 or more went to primary health care for the PHQ-9 and GAD-7. Mild and moderate cases were offered counselling, and severe cases were referred to Civil Hospital Larkana.
The project page lists the work as completed, yet its results section was still marked as to be updated when checked. A thesis can follow the pathway itself. Of the women who screen positive, how many reach assessment, and what stops the rest? Combine interviews with screen-positive women, health workers and Basic Health Unit staff with referral records, if the health department allows access.
The care model behind many such programmes is the WHO’s Problem Management Plus. In a Peshawar trial, 346 adults received five weekly sessions from nine trained lay workers or enhanced care. At three months, 27% of the intervention group met criteria for depression against 59% of the comparison group. Do not screen anyone unless a care route exists, and ask your committee what it requires. The level is MS or MPhil.
7. A repeat survey after repeated glacial floods
Hassanabad residents faced four large glacial lake outburst floods within five years, and 69.84% of the 305 people surveyed had witnessed all four. Women scored higher than men on anxiety, depression and PTSD, and age predicted PTSD. A repeat survey a year or more later, with the same GAD-7, PHQ-9 and IES-R, would show whether symptoms persist. Add exposure measures such as the number of floods witnessed, and keep the stratified sampling frame.
Plan for attrition and for the logistics of a remote valley in Gilgit-Baltistan. This suits an MPhil or PhD, ideally in contact with the original authors, since the figures come from an abstract and not a full paper.
Perinatal and caregiver care in community settings
Community mental health work in Pakistan often runs through Lady Health Workers and peer volunteers. These three topics build on well-documented programmes, so access depends on partnerships.
8. Why some families leave extended peer-delivered perinatal care
In rural Rawalpindi, a five-year report on the peer-delivered Thinking Healthy Programme found that 31 of 45 peer volunteers stayed on and kept their competence. It also found that about a quarter of families did not want to engage over such a long period. Some mothers had problems the peers could not manage, such as interpersonal violence. Women in that setting often depend on husbands and mothers-in-law.
A qualitative study can ask why families leave. Interview mothers who withdrew, plus husbands and mothers-in-law, then analyse the data with framework analysis. Work inside a Lady Health Worker catchment that your health department approves, because the original programme belongs to a research team and access needs a partnership. Prepare a response plan for disclosures of violence. The level is MS or MPhil.
9. Peer competence and retention in an urban low-income setting
The same programme trained peers through a cascade. Specialists trained and supervised non-specialist facilitators, and the facilitators trained and supervised the peers. Competence was rated on six areas, including empathy, family support, content delivery, problem-solving, group facilitation and handling difficult situations. A score of 70% in each area counted as satisfactory, and six peers left because they could not reach that level.
A thesis can ask whether similar retention and competence hold in an urban settlement, where gatekeepers differ. Track the same two outcomes over a defined period, and add interviews on motivation. Ask the authors for permission to use their rating checklist instead of rebuilding it from the six areas, since the programme team developed it. This is an MPhil or PhD design because it involves training and supervising people.
10. Family psychoeducation for schizophrenia with a longer follow-up
In Lahore, Nasr and Kausar randomised 108 patients with schizophrenia and their relatives at Mayo Hospital. The psychoeducation group received nine sessions, and the team measured family burden with the Family Burden Interview Schedule at six months. Burden fell significantly in that group. However, the groups differed at baseline on the routine subscale, so any replication must adjust for baseline scores. The authors also report that most carers were women and that respite care services did not exist.
A replication in another city, with a 12-month follow-up and relapse data alongside burden, would add to this evidence. Analyse it with baseline-adjusted models. Before designing a carer study, read the registration of a multi-centre trial of culturally adapted family and cognitive behavioural interventions for first-episode psychosis. It plans 390 patients across Pakistani cities and lists carer outcomes as secondary aims. Check for overlap early. The level runs from MS to PhD, depending on sample size.
Self-harm research and the law on attempted suicide
These topics need the most care. Both involve distress, and the second sits inside a legal dispute that is still moving. Settle the ethics route before anything else.
11. Attachment, support and self-harm in an age band the original skipped
Haqqani’s 2017 doctoral thesis at Edinburgh translated three scales into Urdu, then surveyed 1,290 school-going adolescents aged 10 to 19. Deliberate self-harm appeared in 7%, counting all intentions. The link between attachment and self-harm ran through social support, depression and anxiety.
A new study can test the same pathway in university students aged 18 to 24, a group the original did not sample. Ask the author before reusing the translated scales, and run mediation models rather than a new translation exercise. Do not ask for method detail from participants. Agree the item wording, the distress protocol and the referral list with your supervisor and committee before any pilot. The level is MPhil or PhD.
12. How clinicians document attempts while the law is unsettled
In May 2026, the Federal Shariat Court struck down the 2022 amendment to the extent that it removed Section 325 of the Pakistan Penal Code, and the section stood restored. The court noted that existing provisions already cover people of unsound mind. In June 2026, the Pakistan Psychiatric Society appealed to the Shariat Appellate Bench of the Supreme Court. The petition argues that the threat of prosecution discourages people from reporting attempts and seeking care. That is the petitioners’ argument, not a finding.
A thesis can interview emergency and psychiatry staff in two or three hospitals about how they record and respond to attempts. Use semi-structured interviews and thematic analysis. Date-stamp every interview with the legal position at that time, so the design survives either outcome of the appeal. Keep hospitals and individuals unidentifiable, because clinicians may fear speaking about practice. The level is MS to PhD.
Position correct as of October 2026; check the Supreme Court of Pakistan’s published orders for the current status of the appeal.
Provincial mental health law and the clinical psychologist’s role
13. Where the Sindh Mental Health Act names psychologists, and where it does not
The Sindh Mental Health Act was passed on 19 September 2013 and assented to on 30 October 2013. Its Authority includes a psychologist with more than ten years of experience. Section 49 sends a person who attempts suicide to an approved psychiatrist, and the Act defines that role as a medical practitioner. Section 56 requires a clinical psychologist at the meeting that decides on psychosurgery. Section 51 requires a psychiatrist or nominated medical officer to obtain written consent before research.
A document analysis can map every clause by the profession it names. Then interview clinical psychologists in Sindh about how those clauses shape daily work. Other provinces have their own acts, so a PhD can compare two of them. Work with a supervisor from law or psychiatry, because a reading of statute is not legal advice.
Position correct as of October 2026 for the 2013 text; check the Provincial Assembly of Sindh for later amendments.
Ethics routes before you collect data
The PHQ-9 includes an item on thoughts of being better off dead or of hurting yourself. Any study that uses it needs a written plan covering who reads the responses, how quickly and where participants are referred. Ask your supervisor for the plan your department already uses.
Published studies can show you how others handled approval. The Urdu GAD-7 study cites approval from the Ethics Review Committee of Khushal Khan Khattak University. The PHQ-9 pregnancy study cites Duke University and the Human Development Research Foundation boards. Cite comparable studies in your application, but follow your own institution’s route.
Trauma and self-harm topics also need a distress protocol and a referral list before the first participant. For studies with psychiatric patients in Sindh, ask your committee how Section 51 applies to a psychologist-led project. If you want a second reader on a proposal and ethics form before the committee sees them, you can ask for a second reader.
Matching a topic to your level
Level changes the question, not only the writing. Use these starting points, then confirm them with your supervisor.
- BS final-year project: topic 1, because it needs questionnaires and classmates but no interviewer.
- MS or MPhil: topics 2, 3, 6, 8, 10, 12 and 13, which need interviews, a clinical rater or a partner site.
- MPhil or PhD: topics 4, 5, 7, 9 and 11, which need larger samples, statistical modelling or a research team.
If none fits, return to the general method for choosing a thesis topic, then narrow one population, one measure set and one setting.
Turning one topic into a proposal
First, check for duplication. Search past PhD theses on the HEC repository, then journals and trial registries. Second, write the question in one sentence with a named population, a named measure and a named setting. Third, draft the plan with the guide to writing the research proposal, and see how a synopsis differs from a proposal if your department asks for a synopsis first.
Questions students ask before choosing
Do I need a clinical interview to validate a screening scale?
You need one to test diagnostic accuracy, because accuracy requires a reference standard such as the SCID or the MINI used in the PHQ-9 studies. Without one, you can still test reliability, factor structure and agreement with other scales.
Can a BS student take a self-harm topic?
That decision belongs to your supervisor and ethics committee. A safer start at BS level is a scale study with no direct questions about self-harm, such as topic 1.
Which topic needs the least access?
Topics 1 and 4 need questionnaires and students. Topic 13 needs documents and a few interviews. Topics 8 to 10 need partner programmes, so they depend on goodwill as much as design.
Where to take your shortlist next
Pick two topics, read the source paper behind each and ask your supervisor which access route is realistic this semester. For PhD work, planning and drafting support for PhD work is available. Support is academic: guidance, structure and feedback, and any model work is for reference and learning, to be used under your institution’s policy. Students who want to see what others say about the service can read the Google reviews.